By Dr. Asnat Raziel, bariatric surgeon specializing in obesity treatment, metabolic health and healthy longevity; Director of the Multidisciplinary Center for Obesity Treatment, Assia Medical, Assuta Ramat HaChayal, Tel Aviv
Obesity treatment: what really works
Obesity treatment today is medical treatment in every sense, not just a matter of willpower. Many of the patients who come to me have tried diet after diet, lost weight and then regained it. That isn’t a personal failure. It is how the body responds to a chronic disease. The good news is that we have effective tools, and combining them in the right way changes the outcome.
In this article, I explain the pillars of treatment, what the research shows about each one, and how to choose the path that is right for you.
Why obesity is a chronic disease
Obesity is not simply a matter of excess calories. It is a disease that involves the brain, hormones, genetics and the environment. To understand obesity and how it is managed, you need to know one key mechanism: the body “fights” to keep the higher weight. I explain this in more detail in my article on obesity as a chronic disease.
In a study published in NEJM, researchers followed 50 people who lost an average of 13.5 kg on a low-calorie diet. Even a year later, their hunger and satiety hormones had not returned to baseline. The hunger hormone ghrelin stayed high, and participants reported increased hunger. That explains why so many people regain weight after a diet. In fact, this is exactly why we need to treat the root of the problem, not just the number on the scale.
The goals of obesity treatment
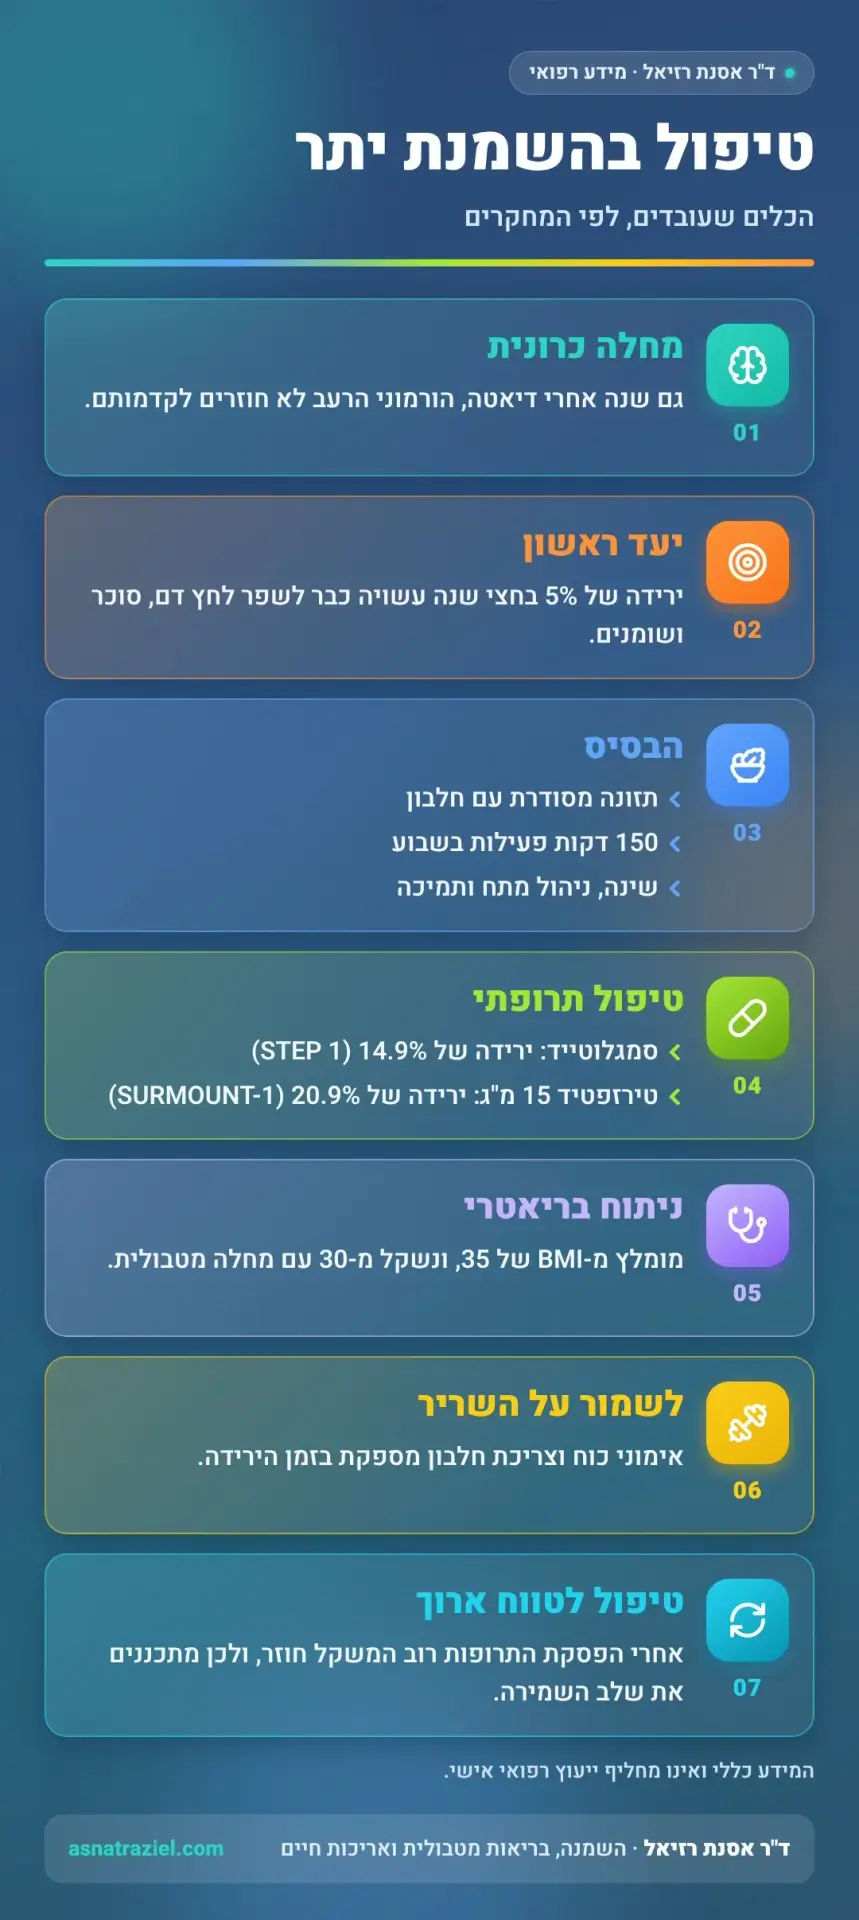
The goal isn’t an “ideal weight.” The goal is good health. The US National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) describes the path to long-term success. According to NIDDK, losing 5% of body weight within six months is a good initial target. For example, a person who weighs 100 kg can first aim to lose 5 kg.
Weight loss of this size may already improve blood pressure, blood sugar and blood lipids. It can also ease knee pain and sleep apnea. On the other hand, some patients need to lose much more weight to treat related conditions. That is why we set a personal target for every patient.
The foundation: nutrition, movement, sleep and support
Every treatment plan starts with lifestyle change. However, this doesn’t mean a crash diet. Effective programs include close support, not just a sheet of instructions. According to NIDDK, a good program includes at least 14 counseling sessions over six months, a tailored eating plan and at least 150 minutes a week of moderate aerobic activity. In addition, it includes daily tracking of food and activity, plus weekly weigh-ins.
- Nutrition: regular meals, protein at every meal, vegetables and fiber, and little processed food.
- Movement: a daily walk and strength training two to three times a week.
- Sleep and stress: short sleep and ongoing stress increase hunger and sugar cravings.
- Emotional support: emotional eating is part of the disease and deserves treatment.
At the same time, it is important to know that exercise alone usually leads to only modest weight loss. In a review by Swift and colleagues, aerobic activity at the recommended level led to an average loss of about 2 kg. Even so, the benefits for the heart, the muscles and mood are far greater than the number on the scale suggests.
Medication as part of obesity treatment
The new medications have changed the picture. They act on the hunger and satiety centers in the brain and reduce “food noise” and appetite. As a result, sticking with new habits becomes much easier. It is worth learning how obesity medication works before you start.
In the STEP 1 trial, semaglutide, sold as Wegovy, led to an average weight loss of 14.9% after 68 weeks, compared with 2.4% in the placebo group. In the SURMOUNT-1 trial, tirzepatide, sold as Mounjaro, led to a 20.9% weight loss at the 15 mg dose after 72 weeks. Following these results, the US FDA announced the approval of tirzepatide for chronic weight management under the brand name Zepbound.
These medications are intended for adults with a BMI of 30 or more, or 27 or more with a related condition such as high blood pressure or diabetes. The most common side effects are nausea, constipation and diarrhea, mainly at the start of treatment. For this reason, doctors increase the dose gradually and monitor patients closely. My guide to obesity medication covers the options in more detail.
Bariatric surgery as part of obesity treatment
Bariatric surgery still leads to the largest and most durable weight loss. The 2022 joint guidelines of the international bariatric surgery societies recommend surgery from a BMI of 35, even without related conditions. In addition, surgeons consider surgery from a BMI of 30 in people with a metabolic disease such as type 2 diabetes.
The Swedish SOS study followed about 4,000 people for an average of about 11 years. After ten years, those who had surgery maintained a weight loss of 14% to 25%. Moreover, overall mortality in the surgery group was lower than in the control group. Today, we often combine surgery and medication, depending on each patient’s needs.
Protecting your muscles while you lose weight
Whenever weight comes off quickly, part of the weight lost is muscle. Muscle matters for metabolism, strength and quality of life, especially after age 50. So I recommend strength training and enough protein to every patient. You can read more about preserving muscle mass during weight loss.
Obesity treatment is long-term treatment
As with high blood pressure or diabetes, treatment doesn’t end when you reach your goal. In the STEP 1 extension, participants who stopped semaglutide regained about two-thirds of the weight they had lost within a year. Similarly, in the SURMOUNT-4 trial, those who stopped tirzepatide regained 14.0% of their body weight, while those who continued lost another 5.5%.
The message is simple: you need a plan for the maintenance phase, not just for the weight-loss phase. Sometimes that means continuing medication, and sometimes a lower dose with close follow-up. Either way, the doctor and the patient make this decision together. Managing treatment over the years is also part of the plan. If you are thinking about it, read my guide to stopping weight-loss medication.
How to choose the right obesity treatment for you
No single treatment suits everyone. The choice depends on BMI, related conditions, age, preferences and past experience. That is why the assessment starts with an in-depth conversation, blood tests and a body composition measurement. Next, a team of a doctor, a dietitian, a psychologist and a fitness coach builds the plan. This is how multidisciplinary obesity medicine works.
In our clinic, we see again and again that combining medical treatment with habit change leads to the best results. It is worth seeing a doctor who specializes in obesity medicine and knows all the options. The field is also moving very fast, and it pays to keep an eye on what the next decade of obesity medicine will bring.
Bottom line
Obesity treatment succeeds when we treat obesity as a chronic disease. The foundation is nutrition, movement, sleep and support. On top of that foundation, new medications and bariatric surgery make significant weight loss and better health possible. Ultimately, success depends on a personal plan, protecting your muscles and long-term follow-up.
This article provides general information and is not a substitute for personal medical advice.
Questions and answers
When should I seek obesity treatment?
When your BMI is 30 or more, or 27 or more with a related condition. It is also worth seeking help if previous attempts didn’t last.
How much weight do I need to lose to feel a difference?
Losing 5% of your body weight may already improve blood pressure, blood sugar and blood lipids. Losing more usually brings additional benefits.
Can I stop the medication once I reach my goal?
You can, but research shows that most patients regain weight after stopping. So make this decision together with your doctor, with a clear maintenance plan.
Is surgery better than medication?
Not always. Surgery leads to large and lasting weight loss, but medication suits many people. The decision depends on each patient’s health and preferences.
Sources
Treatment for Overweight & Obesity – NIDDK
Long-term persistence of hormonal adaptations to weight loss
Once-Weekly Semaglutide in Adults with Overweight or Obesity
Tirzepatide Once Weekly for the Treatment of Obesity
FDA Approves New Medication for Chronic Weight Management
Effects of bariatric surgery on mortality in Swedish obese subjects
The role of exercise and physical activity in weight loss and maintenance




